How to Build Your FET Timeline (Even When Your Protocol Keeps Changing)

A frozen embryo transfer (FET) timeline can feel difficult to follow because it is not always a fixed calendar. Monitoring results, hormone levels, ovulation, lining development, embryo stage, and clinic decisions can all affect what happens next.
The most useful timeline is not the one that predicts every date months in advance. It is the one that clearly separates what is confirmed, what is being monitored, and what still depends on your care team.
Use this article and planner as a place to write down, record, and keep track of what your clinic says without trying to make medical decisions yourself. Your fertility clinic should determine your protocol, medication plan, monitoring schedule, transfer date, and pregnancy testing instructions.
Important: This article is for organization and general education only. It is not medical advice. Do not start, stop, change, or delay medication based on this information. Ask your fertility clinic to review anything that affects your individual treatment.
Start with the Timeline Anchors
Begin by recording the dates your clinic has already confirmed. These may include:
- Your cycle start date, if your clinic uses cycle-based planning
- Your baseline ultrasound or bloodwork
- Monitoring appointments
- Medication start or change dates
- The date your clinic expects to confirm the transfer plan
- Embryo transfer
- Pregnancy testing
- Follow-up appointments
Leave space between these anchors. Do not fill every day with assumptions.
A clinic may provide an estimated transfer date and later adjust it after monitoring. That change does not mean your entire cycle has failed. It usually means your care team is using new information to make the next decision.
Clinical guidance from UW Medicine’s embryo transfer education materials explains that FET timing is connected to the preparation of the uterine lining, hormone exposure, ovulation, and embryo development. These details are why your clinic’s written calendar should remain the primary source for your cycle.
Understand Your Type of FET Cycle
Your clinic may describe your cycle as natural, modified-natural, programmed, medicated, or hormone replacement. The names and details can vary between clinics, but the basic differences are useful to understand.
The evidence does not establish one preparation method as the best choice for every patient. A Cochrane review on endometrial preparation notes that available research has limitations and that treatment decisions depend on individual circumstances and clinical judgment.
| FET Cycle Type | Core Mechanism | Primary Monitoring Factors |
|---|---|---|
| Natural | Uses your body's ovulation to help time the transfer. | Follicle growth, luteinizing hormone (LH) changes, and lining thickness. |
| Modified-Natural | Follows natural development and may use an injection to help time ovulation. | Follicle development and clinic monitoring to plan the trigger and transfer dates. |
| Programmed / Medicated | Uses prescribed hormones (estrogen and progesterone) to build and prepare the lining. | Uterine lining thickness and the timing of the first progesterone dose according to your clinic's instructions. |
Special Note on Programmed Cycles
In a programmed cycle, the relationship between progesterone exposure and embryo transfer is especially important. Record the exact instructions your clinic gives you, including the date, time, and route. Ask your clinic in advance for specific instructions on what to do if a dose is late or missed so you know exactly how to react without panic.
Build Your Timeline in Three Layers
A three-layer system can make changing plans easier to follow. Use different colors or visual symbols for each section to prevent estimates from looking final.
1. Confirmed
Record information that your clinic has clearly finalized.
- Appointment dates and times
- Medication instructions currently in use
- The embryo selected for transfer
- A confirmed transfer date or pregnancy test date
- Official instructions provided in writing through your patient portal
2. Expected
Record dates that are highly likely but still subject to change based on your body's response.
- The next monitoring appointment window
- A tentative lining check date
- An estimated transfer window provided at the start of the cycle
- A scheduled medication review or a tentative follow-up call
3. Questions or Decisions Pending
Create a dedicated, separate space for items that require immediate clarification from your care team.
- Whether a medication continues or stops after a calendar date changes
- How your clinic counts treatment days
- What to do if bleeding begins before your scheduled test
- Specific clinic protocol for a missed or late medication dose
Track Information Instead of Predicting Outcomes
A FET planner should give you one centralized place to record what happened and what your clinic said. It should never replace clinical judgment.
Useful items to track include:
- Clinic data: Appointment dates, locations, and verbal instructions received over the phone.
- Lab metrics: Ultrasound measurements and blood test values exactly as reported by the clinic.
- Medication logs: Exact name, dose, route, and the specific time a medication was taken.
- Communication: Questions sent through the patient portal and the answers received.
Clinical Tip: For lab results, record the value exactly as provided and include the date and units when available. Avoid interpreting the result yourself or comparing your values to online forums. Add a note such as “review with clinic” if you are unsure what a specific number means. The same applies to symptoms; a planner can help you note changes to discuss with your nurse, but it cannot determine if a symptom is expected.

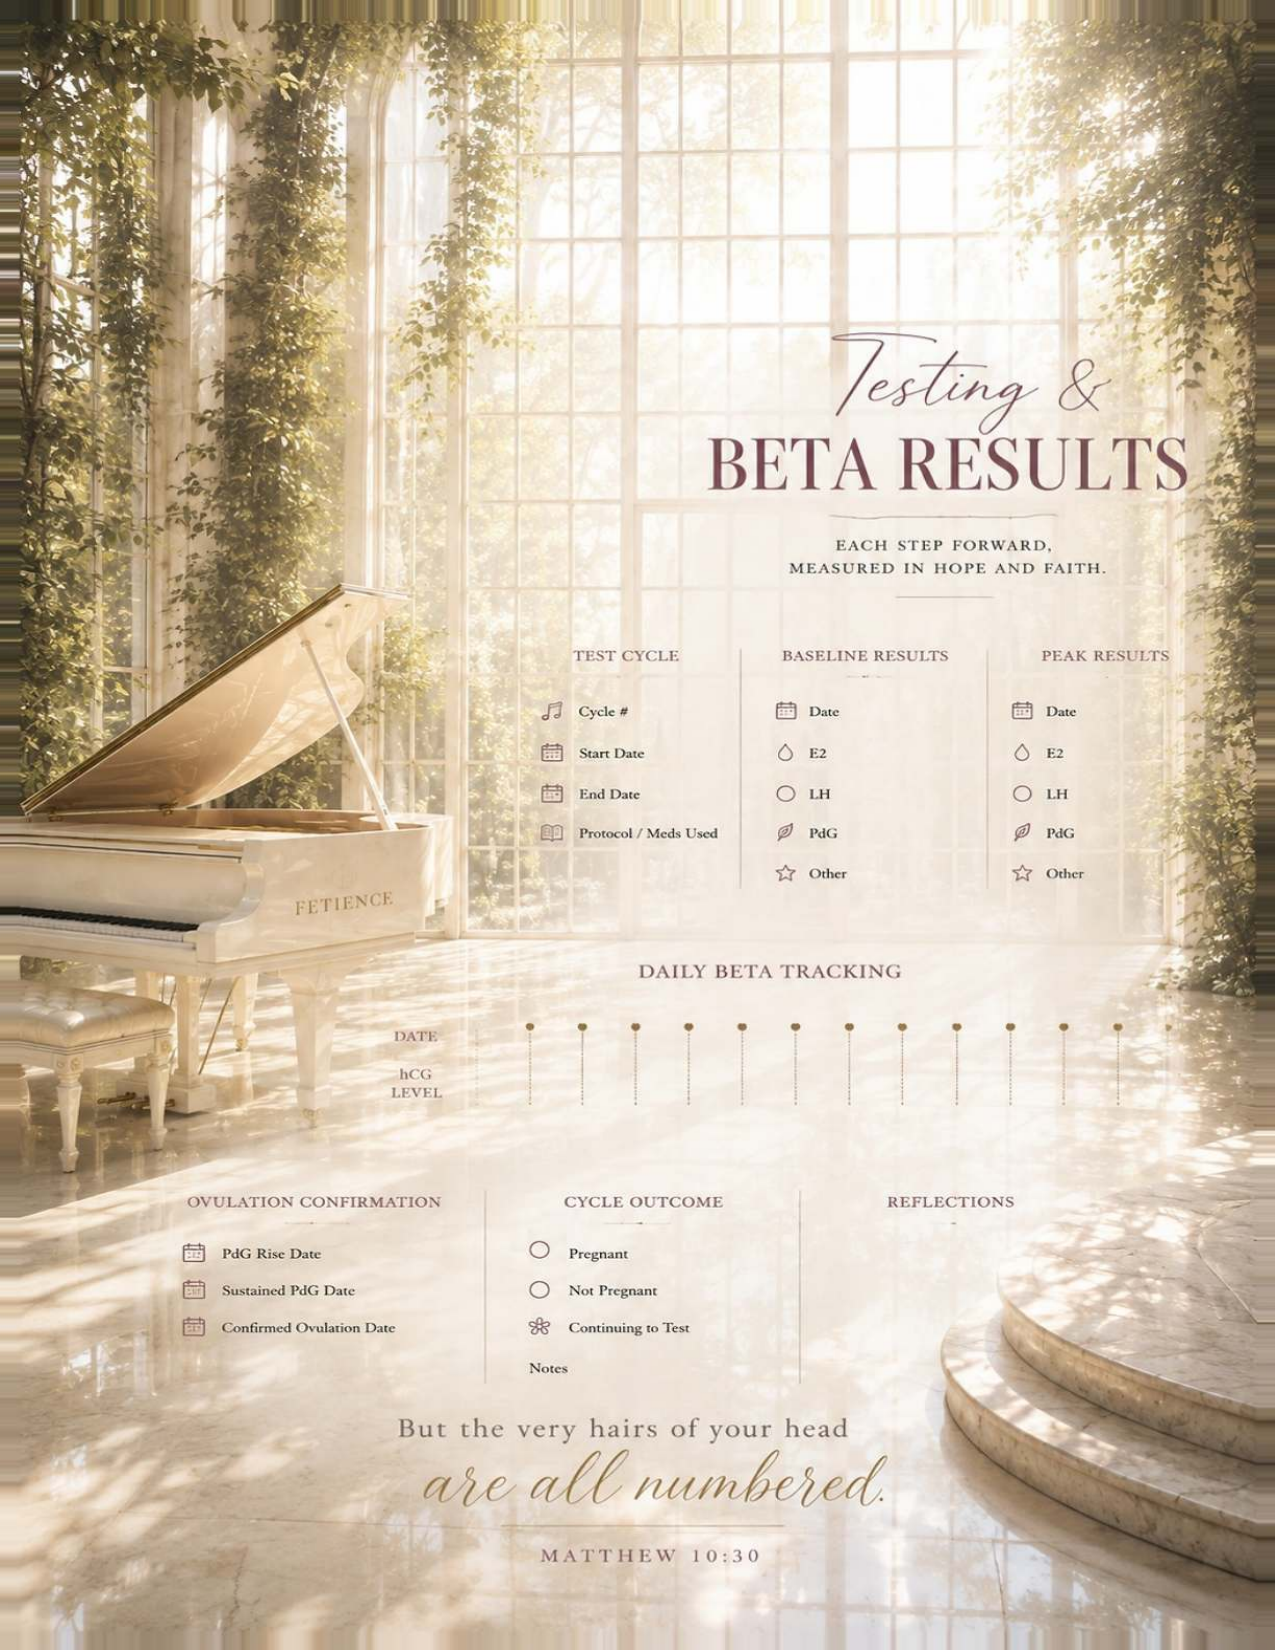
Understanding Pregnancy Testing and “Beta” Results
The final milestone on your FET timeline is the pregnancy test. Some fertility clinics use a quantitative blood test called a Beta hCG test (often just called a “Beta”); others ask you to use a home pregnancy test on a specified date. A blood test measures the amount of human chorionic gonadotropin (hCG) in your bloodstream.
When tracking your testing milestone, keep these clinical principles in mind:
- Follow Your Test Date: Your clinic will give you a specific date and tell you whether to use a home test or have blood drawn. Testing too early can give a misleading result, including a positive result from hCG used in a trigger injection. Follow the date and instructions your care team provides.
- Line Darkness Does Not Measure Progression: At-home urine tests detect hCG, but the darkness of a test line cannot reliably measure how a pregnancy is progressing. Urine concentration and differences between tests can change how the line looks. Ask your care team how they will assess your result.
- One Beta Result Is Not the Whole Picture: If your clinic orders a blood test, one hCG value may not answer every question. hCG can rise at different rates, and a strict “doubling time” rule cannot determine on its own whether a pregnancy is viable.
- Follow-Up Depends on Your Result: Your care team may recommend another blood test, an ultrasound, or other follow-up based on your result and circumstances. Record the plan they give you rather than comparing your numbers with someone else's.
Write down your numbers, dates, and measurement units in your planner exactly as the clinic gives them to you. Resist the urge to compare your initial baseline or your exact doubling hours to numbers on internet forums, as every individual timeline and embryo develops at its own pace.
For more detail, see Gateshead Health's pregnancy-test guidance, Newcastle Hospitals' home-test guidance, and research on variation in hCG rise.
Create a Change Log
When your protocol changes, add a short entry rather than erasing the original information. This keeps your records accurate if you receive several updates in a short period.
A useful change log entry includes:
- Date and time of the update
- What changed (and which old instruction is no longer current)
- Who provided the update
- Your immediate next question or follow-up step
Example Entry: October 12: Clinic updated monitoring plan after appointment. Transfer date is now pending. Continue only according to the written medication instructions. Confirm next appointment time through the patient portal.
A review in the journal Frontiers in Endocrinology describes meaningful variation between FET protocols, including how clinics monitor ovulation, prepare the lining, provide hormone support, and calculate transfer timing. A changing calendar is therefore not unusual. The relevant question is whether you have the most current instructions from your care team.

The paid digital planner can travel with you through more than one cycle. Print its treatment tracking pages again whenever you need a fresh copy.
Explore the planners: FETience IVF/FET Digital Planner · 7-Page FET Planner ($9.95)